What 'First in Human' Actually Means: Decoding Phase One Research Trials
Over the course of my career, I've worked across the full spectrum of clinical drug development from large multi-center trials down to the earliest stages of human testing. Across all of that work, there is one phrase that understandably makes potential participants pause: first in human.
I get it. If someone tells you that you may be among the very first people to receive an investigational drug, it can sound like a compound was synthesized on a laboratory bench, placed in a syringe, and given to a person while researchers stand around waiting to see what happens.
That is not how it works. First-in-human research does involve genuine uncertainty, and there is no honest way to discuss clinical research without saying that clearly. Unexpected side effects can happen in Phase 1 trials. They can also happen in Phase 2 and Phase 3 trials—and, occasionally, only become apparent after a drug has been FDA-approved and used much more widely.
But “first in human” does not mean “untested.” By the time an investigational drug reaches its first human participant, a tremendous amount of work has already taken place. Once that initial dose is given, the study is designed to proceed deliberately, with multiple layers of safety monitoring built directly around the uncertainty that remains.
Before the First Human Dose
Drug development begins long before the first participant walks into a research site. Before an investigational medication can be studied in people, researchers conduct extensive preclinical testing to learn as much as they reasonably can about both the drug and its potential risks.1
Depending on the therapy, this may include laboratory and animal studies examining how the drug behaves in the body, how it is metabolized and eliminated, and what toxic effects appear at different levels of exposure. Researchers aren't simply asking whether the drug works. They are asking specific, critical safety questions:
- Which organ systems might be affected?
- At what exposure do concerning effects begin to appear, and are those effects reversible?
- What happens as exposure increases?
- Is there enough of a safety margin to justify taking the next step into human trials?
That information becomes part of the package submitted to the U.S. Food and Drug Administration through an Investigational New Drug application, or IND.2 For many traditional drugs, researchers use those preclinical data to estimate an appropriate human starting dose and incorporate a safety factor or margin.3 In other words, the starting dose isn't a guess—it is intentionally conservative because uncertainty still exists.
Oversight Before We Ever Give the Drug
There are multiple layers of independent oversight between preclinical testing and the person sitting in the research chair. The FDA reviews the IND, including the available preclinical safety data, manufacturing information, and the proposed clinical protocol. Following an initial IND submission, the IND generally becomes effective 30 calendar days after FDA receives it, unless FDA places the study on clinical hold or notifies the sponsor earlier that the investigation may begin.4,5
Then there is another essential layer: the Institutional Review Board, or IRB. With the protection of human participants at the center of its review, the IRB independently evaluates the research ethics, the balance of risks and potential benefits, equitable subject selection, informed consent documents, and participant safeguards.1,6 The IRB can require changes to the protocol, consent materials, or other aspects of the research before granting approval.
By the time someone at a research site sits down with you to discuss participating, the study has already undergone substantial scientific, regulatory, and ethical review. That doesn't mean someone has determined that nothing bad can happen. It means independent regulatory and ethical groups have evaluated whether the available evidence and safeguards make it reasonable to proceed. That is a vital distinction.
What Actually Happens Inside the Unit
This is the part of early-phase research I wish more potential participants could see before deciding whether “Phase 1” sounds too frightening, because the day-to-day reality inside the unit is often very different from what people imagine. We don't bring in a large group of people, give everyone an investigational drug at once, and wait to see what happens. Early-phase research is designed to learn a little, evaluate the data, and then decide whether it is appropriate to move forward.
Many Phase 1 studies use sequential dose cohorts. A small group of participants receives a specific low dose, and their safety data and drug exposure are evaluated according to the protocol. If the predefined criteria for moving forward are met, another cohort may receive a higher dose. Dosing within a single cohort is often staggered as well, meaning the first participant—or a small subset—is dosed before the remainder of the group.7 This approach means that if an unexpected reaction occurs, fewer people may have been exposed before the research team has the opportunity to evaluate and respond.
Safety isn't left to a vague instruction to “monitor the participant closely.” Clinical protocols specify exactly which laboratory tests are required, how often vital signs must be checked, when ECGs are performed, what symptoms require additional medical evaluation, and what specific findings prevent dose escalation. Depending on the study, there may also be predefined stopping or pausing criteria for an individual participant, a cohort, or the study as a whole. The goal is to anticipate safety decisions before we are in the middle of making them, providing a clear operational framework if something unexpected occurs.
You Are Watched Closely
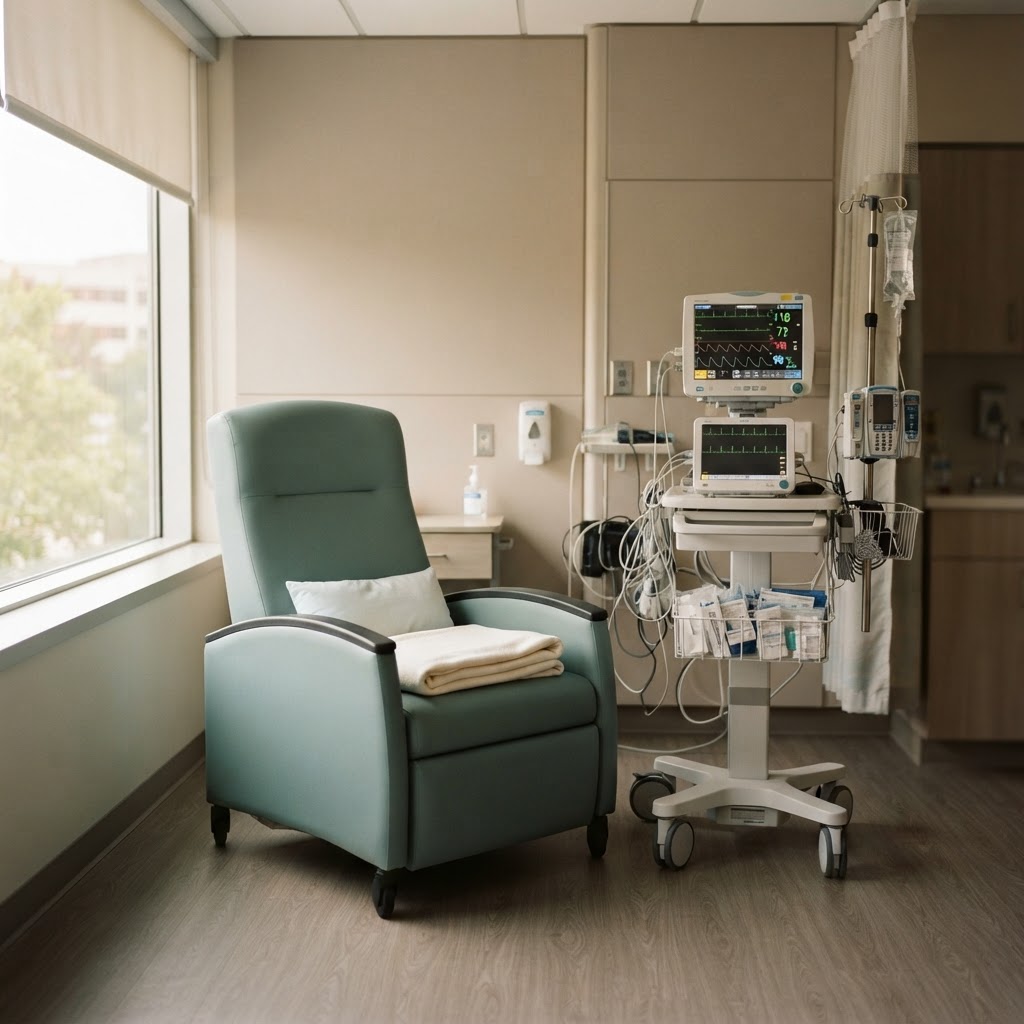
If you participate in a Phase 1 study, you will likely be surprised by the sheer volume of monitoring that happens after dosing. On some studies, we might check your vital signs before dosing, then again 15 or 30 minutes later, an hour later, and repeatedly throughout the day.
There are often serial ECGs and multiple blood draws. Some of those blood samples are standard safety labs, while others are pharmacokinetic samples—often referred to as PK draws. PK samples allow us to measure the concentration of the drug in your bloodstream at specific points in time. They answer fundamental questions about how quickly the drug appears in the bloodstream, how high the concentration gets, how long it stays there, and how quickly your body clears it.8
At the same time, we are watching you as a person. Blood pressures, ECGs, labs, and PK samples can make Phase 1 sound like participants are merely specimens under observation, but the research team in the room is not only looking at the numbers. We want to know how you feel, whether your blood pressure or heart rate has shifted, whether you look okay, and whether anything is happening that we didn't expect. This is where the predictions made during preclinical testing meet actual human biology, and we pay exceptionally close attention to that transition.
Phase 1 Does Not Always Mean “First in Human”
It is worth clarifying that “Phase 1” and “first in human” are not synonymous, though the terms are often used interchangeably. Phase 1 describes a broad stage of clinical development focused heavily on safety, tolerability, pharmacokinetics, and dose selection.8 While a particular Phase 1 study may include the very first humans ever to receive a drug, another Phase 1 participant might enroll after multiple cohorts have already been treated. There may even have been a previous early-phase study of the same drug in a different population.
The first participant in a first-in-human trial really may be entering territory no human has entered before. Participant 40 is in a distinctly different position. By that point, researchers may already have pharmacokinetic and safety data from dozens of people at lower doses. Safety information is continually collected across research sites and communicated through the sponsor. Certain serious or otherwise significant new safety findings trigger expedited regulatory reporting, and accumulating safety information may also lead to updates to the Investigator's Brochure, consent documents, monitoring procedures, or protocol.1,9 The safety assessment never ends when the trial begins—it continues throughout development.
If you are considering a Phase 1 trial, one of the most practical questions you can ask is simple: How many people have received this drug before me? You are always allowed to ask.
Is Phase 1 Research Safe?
This is the central question people want answered, and no one working in clinical research should answer it with a simple “yes.” Phase 1 research carries inherent risk. Preclinical studies cannot perfectly predict human biology, some adverse reactions are unexpected, rare events may only become apparent when many more people are exposed, and serious outcomes can occur.
That reality exists beyond Phase 1 as well. Uncommon adverse effects can emerge in Phase 3 clinical trials and even post-marketing, after FDA approval, when medications are used by vast and diverse populations. Medicine never offers zero risk.
What Phase 1 research does is acknowledge that the initial uncertainty is higher—and explicitly builds the study around that fact. Uncertainty is not the same thing as recklessness. The reason we use small cohorts, conservative starting doses, intensive real-time monitoring, predefined escalation criteria, independent IRB review, and extensive preclinical testing is precisely because researchers know there are things we do not yet know. The safeguards exist because of the uncertainty, not because anyone is pretending it isn't there.
Ask Questions Before Deciding
During informed consent, the study team should explain the research and give you time to ask questions before you decide whether to participate.1 If you're considering an early-phase study, here are some questions to ask:
- How many humans have received this drug so far, and at what doses?
- What did researchers observe in the preclinical animal studies?
- What specific side effects are you watching for in this cohort?
- How was the dose I'll receive selected?
- Will dosing be staggered between participants?
- What specific findings would cause my dosing to stop, or cause the entire study to pause?
- What medical care is available on-site if I experience a reaction?
If you are considering being among the very first humans to receive a drug, express your specific concerns directly. I would much rather have a potential participant ask difficult, pointed questions than agree to enroll while quietly terrified because they think they are simply supposed to trust us. You do not owe a clinical trial your participation. Our job as investigators is to provide you with enough clear data and context so that you can decide whether participation makes sense for your life.
Those three words—first in human—sound frightening because they highlight what we do not know. That unknown is real, and it is the entire reason the research exists. But what the phrase leaves out is the surrounding structure: the years of preclinical science, the dose calculations, the regulatory reviews, the protocol design, the small cohorts, the repeated safety checks, and the team of researchers in the unit watching every step unfold in real time.
If you're considering a first-in-human study, I hope knowing more about the process makes it feel less intimidating. Ask your questions, meet the team, and take the time you need to decide. You should feel comfortable with the people caring for you and understand how they plan to keep you safe. As an investigator, I take that responsibility seriously. We're there to learn about a new treatment, but we're also there to care for the person who has trusted us enough to participate.
References
- International Council for Harmonisation of Technical Requirements for Pharmaceuticals for Human Use. ICH Harmonised Guideline: Good Clinical Practice E6(R3). Adopted January 6, 2025. Accessed October 2, 2026. https://database.ich.org/sites/default/files/ICH_E6(R3)_Step4_FinalGuideline_2025_0106.pdf
- IND content and format, 21 CFR §312.23. Accessed October 2, 2026. https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/section-312.23
- US Food and Drug Administration. Estimating the Maximum Safe Starting Dose in Initial Clinical Trials for Therapeutics in Adult Healthy Volunteers: Guidance for Industry. Published July 2005. Accessed October 2, 2026. https://www.fda.gov/media/72309/download
- General requirements for use of an investigational new drug in a clinical investigation, 21 CFR §312.40. Accessed October 2, 2026. https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/section-312.40
- Clinical holds and requests for modification, 21 CFR §312.42. Accessed October 2, 2026. https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/section-312.42
- Criteria for IRB approval of research, 21 CFR §56.111. Accessed October 2, 2026. https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-56/section-56.111
- European Medicines Agency. Guideline on Strategies to Identify and Mitigate Risks for First-in-Human and Early Clinical Trials With Investigational Medicinal Products. EMEA/CHMP/SWP/28367/07 Rev. 1. Published July 20, 2017. Accessed October 2, 2026. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-strategies-identify-and-mitigate-risks-first-human-and-early-clinical-trials-investigational-medicinal-products-revision-1_en.pdf
- Phases of an investigation, 21 CFR §312.21. Accessed October 2, 2026. https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/section-312.21
- IND safety reporting, 21 CFR §312.32. Accessed October 2, 2026. https://www.ecfr.gov/current/title-21/chapter-I/subchapter-D/part-312/section-312.32
Get new articles in your inbox
Join readers who want clarity on dementia research — without having to read the journals themselves.
This article is provided for informational and educational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional for questions about diagnosis, treatment, or your personal health.